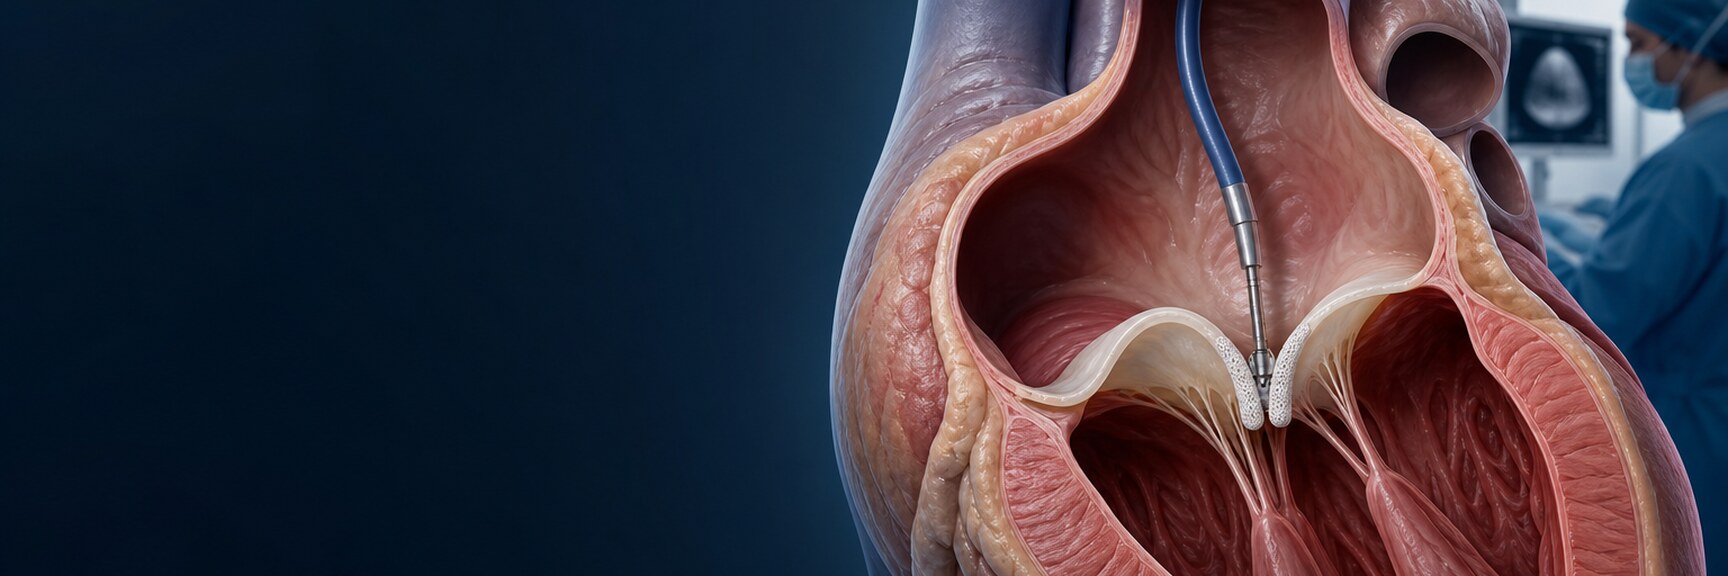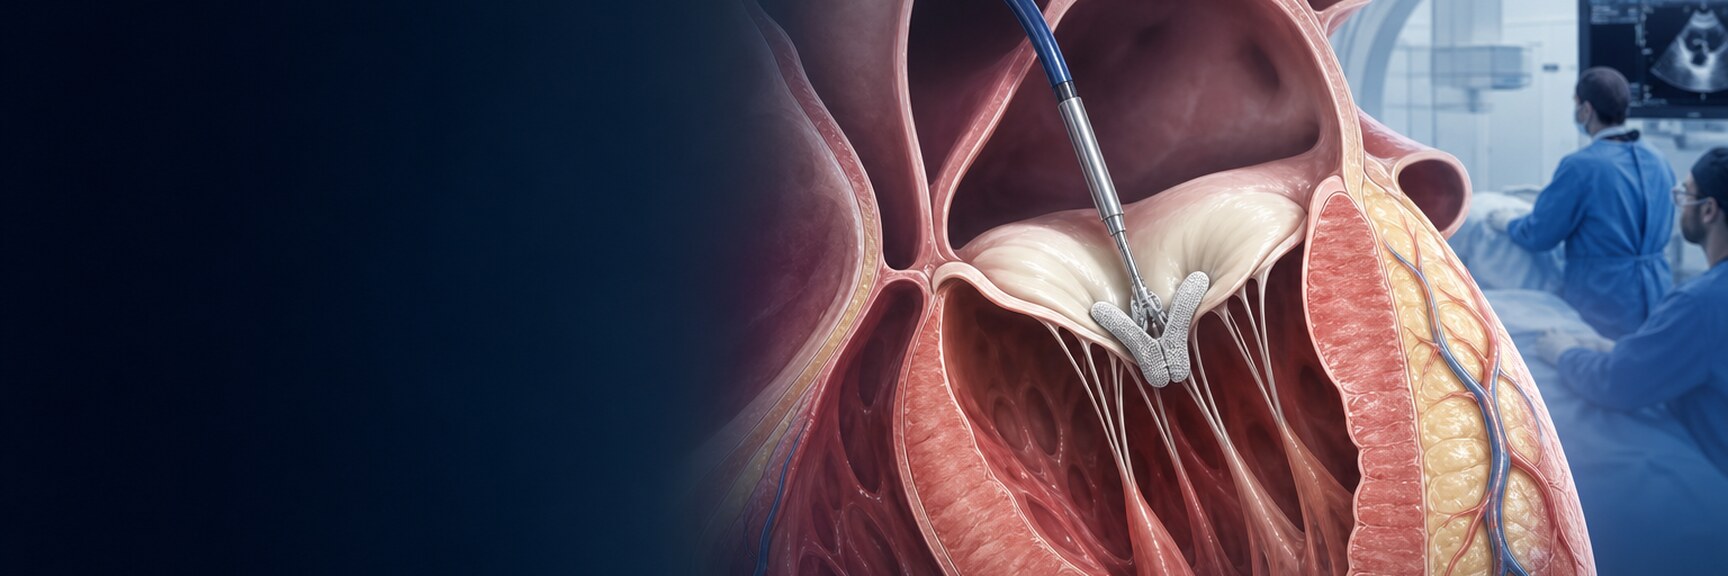

MitraClip is one of the device systems used for mitral transcatheter edge-to-edge repair (M-TEER). The native valve is not removed. A catheter is advanced from a femoral vein and selected mitral leaflets are brought together to improve closure and reduce backward blood flow.[1–3]
What is mitral regurgitation?
The mitral valve lies between the left atrium and left ventricle. When its leaflets do not close properly, blood leaks backward during ventricular contraction. Possible symptoms include breathlessness, reduced exercise capacity, fatigue, swelling, palpitations and repeated heart-failure admissions. These symptoms are not specific to the valve and require clinical and imaging assessment.
Why are primary and secondary mitral regurgitation separated?
In primary mitral regurgitation, the main problem is in the leaflets, chords or other valve structures. When durable repair is expected in an appropriate surgical candidate, surgical repair is the established treatment.[1]
In secondary mitral regurgitation, ventricular or atrial remodelling prevents otherwise less structurally diseased leaflets from closing effectively. In ventricular secondary mitral regurgitation, guideline-directed heart-failure treatment and cardiac resynchronisation therapy when indicated are optimised before M-TEER is considered.[1,2]

Are M-TEER and MitraClip the same thing?
M-TEER is the general procedure. MitraClip is one device system used to perform it, while PASCAL is another. M-TEER is not the same as transcatheter mitral valve replacement: M-TEER repairs by approximating leaflets, whereas replacement places a prosthetic valve.
Who may be assessed for MitraClip?
Primary mitral regurgitation
For operable severe primary mitral regurgitation with a high probability of durable repair, surgery remains the preferred treatment. M-TEER may be assessed in selected symptomatic patients whose anatomy is suitable and whose surgical risk is high or prohibitive according to the Heart Team.[1,2]
Ventricular secondary mitral regurgitation
Medical therapy is first optimised and CRT is considered when indicated. M-TEER may then be considered in selected patients with persistent symptoms and severe regurgitation. Factors associated with a greater chance of benefit include suitable anatomy, NYHA class II or worse symptoms, LVEF 20–50%, LV end-systolic diameter no greater than 70 mm, recent heart-failure admission or raised natriuretic peptides, pulmonary systolic pressure no greater than 70 mmHg, and no advanced right-heart or end-stage heart failure.[1]
These are not a self-assessment checklist. The Heart Team interprets the complete clinical picture.

How is a patient assessed before MitraClip?
Transthoracic echocardiography assesses regurgitation mechanism and severity, chamber size, ventricular function, pulmonary pressure and other valves. Transoesophageal echocardiography provides detailed information about leaflet length and movement, prolapse or flail, coaptation, calcification, jet location, valve area and baseline gradient. It is also used for intraprocedural guidance.[1,3]
The team also reviews heart-failure treatment, rhythm, kidney and lung function, frailty, life expectancy, coronary disease and whether another cardiac intervention is needed. The question is not merely whether a device can be implanted but whether the procedure is likely to provide meaningful benefit.[1,2]
How is the MitraClip procedure performed?
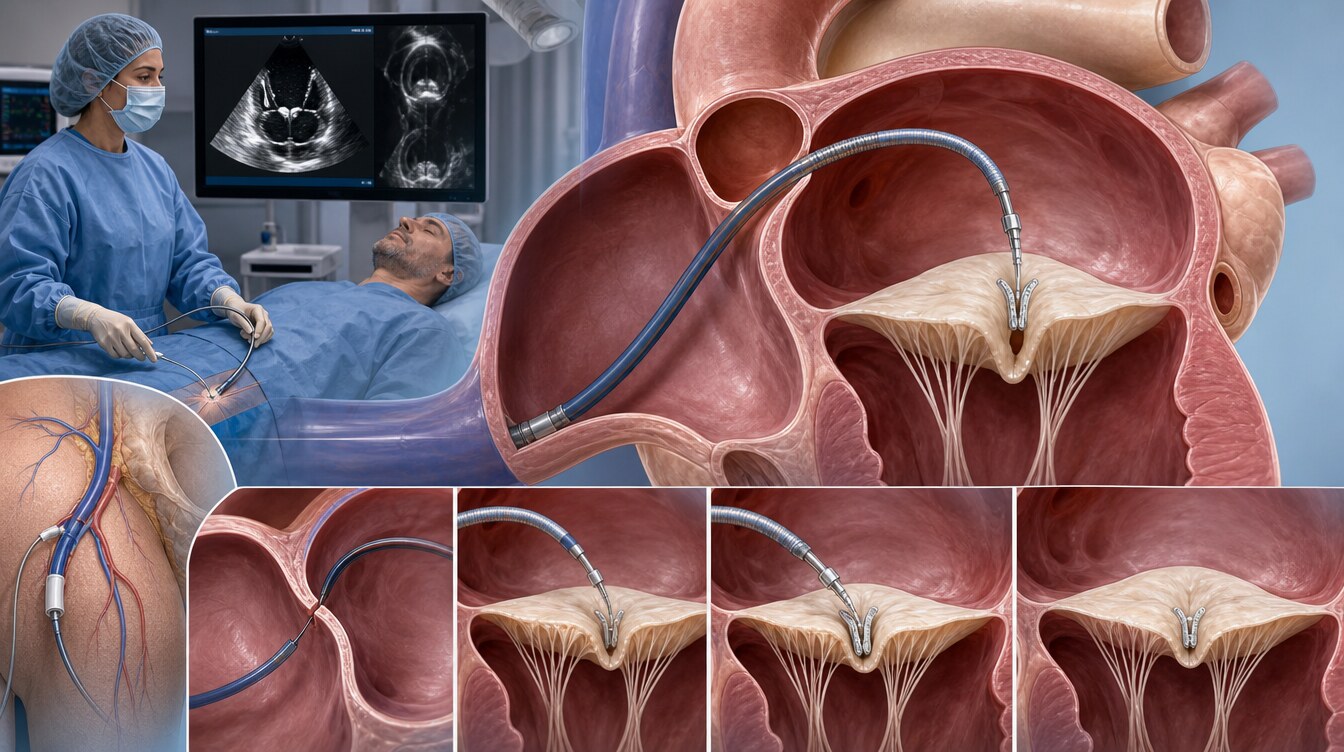
Details vary with anatomy and centre protocol. In general:
- The patient, medicines, fasting and anaesthesia plan are reviewed.
- Venous access is obtained through the groin.
- The catheter passes from the right to the left atrium through a controlled transseptal puncture.
- The delivery system is directed toward the mitral valve using transoesophageal echocardiography and fluoroscopy.
- Suitable leaflet segments are captured and the effect on regurgitation and valve gradient is checked.
- More than one implant may be used when anatomy and the result require it.
- Leaflet attachment, residual regurgitation and gradient are reassessed before the catheter is removed.
Avoiding sternotomy and cardiopulmonary bypass does not make the procedure simple or risk-free. General anaesthesia is commonly used, although protocols vary.[1,16]
What benefit may be expected?
In appropriately selected patients, the goals are to reduce regurgitation, improve breathlessness and functional capacity, support quality of life and, in some secondary-mitral-regurgitation groups, reduce heart-failure admissions. Benefit depends on mechanism, myocardial disease, procedural result and other illness.[1,5–9]
Why did major trials report different results?
COAPT. In carefully selected patients with heart failure and moderate-to-severe or severe secondary mitral regurgitation whose symptoms persisted despite guideline-directed medical therapy, M-TEER plus medical therapy reduced heart-failure hospitalisations compared with medical therapy alone. At five years, all-cause mortality was also lower. These findings should not be generalised to every patient with mitral regurgitation.[5,6]
MITRA-FR. In a population with secondary mitral regurgitation and heart failure, M-TEER did not show a significant advantage for death or unplanned heart-failure hospitalisation at one or two years. That result should not be restated as an absolute claim that “MitraClip does not work.”[7,8]
RESHAPE-HF2. In patients with functional/secondary mitral regurgitation and heart failure, the composite of first or recurrent heart-failure hospitalisation or cardiovascular death at 24 months was lower in the M-TEER arm. The difference was driven mainly by fewer heart-failure hospitalisations, and health status improved. A significant reduction in isolated cardiovascular mortality should not be claimed.[9]
Different results between COAPT and MITRA-FR cannot be explained by a single factor. Within the 2025 ESC/EACTS framework, patient selection; the relationship between regurgitation severity and left-ventricular remodelling; left-ventricular size and disease stage; how guideline-directed medical therapy was applied; echocardiographic assessment of regurgitation; procedural/technical success; and differences in trial design and follow-up are interpreted together. The “disproportionate” versus “proportionate” mitral-regurgitation distinction has been discussed as a possible phenotypic hypothesis and should not be presented as the sole proven cause of the divergent results.[1]
The 2025 ESC/EACTS guidelines have strengthened the role of M-TEER, in light of contemporary randomised evidence, for selected patients with severe ventricular secondary mitral regurgitation who remain symptomatic despite guideline-directed medical therapy and who meet defined clinical criteria. This is not an automatic indication for everyone, and atrial secondary mitral regurgitation is not placed at the same evidence level.[1]
MitraClip or surgical repair?
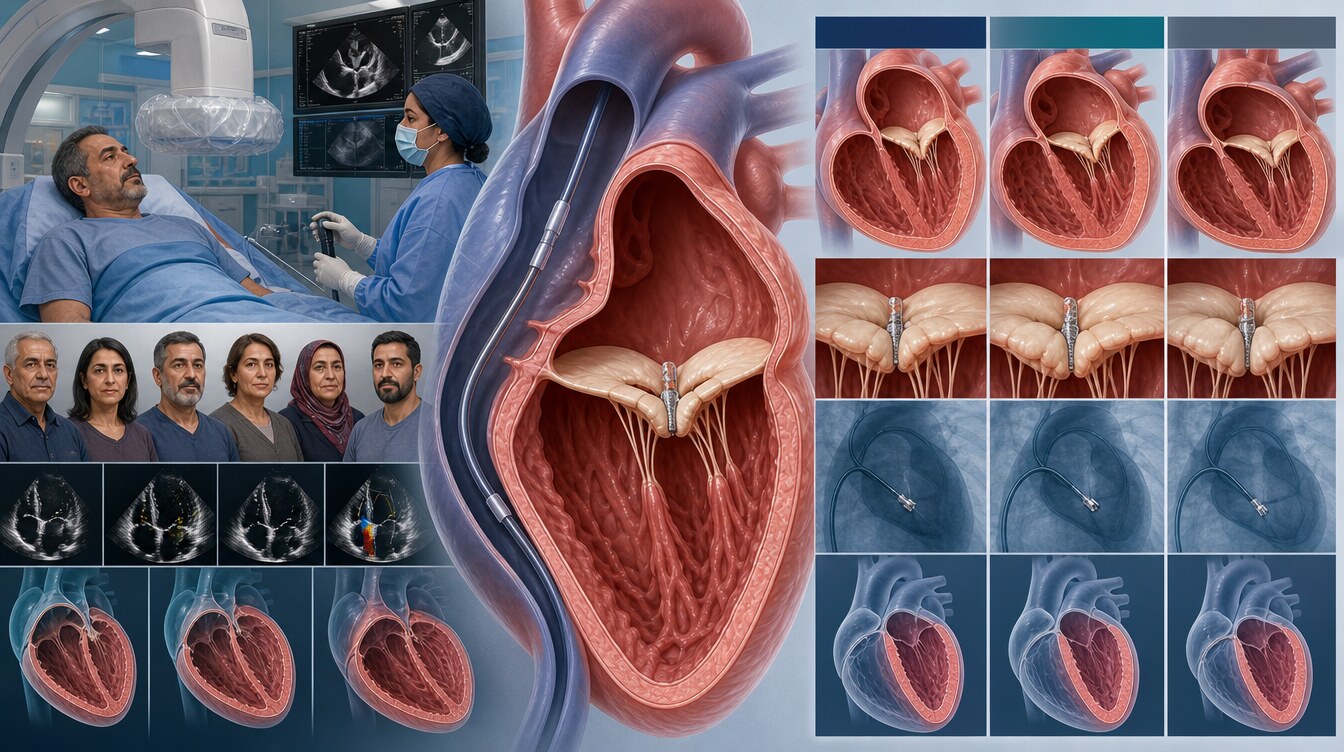
Surgical repair remains the established option for an appropriate surgical candidate with primary mitral regurgitation when durable repair is expected.[1] Frailty, organ function, previous surgery, valve anatomy and patient preference are considered with age rather than age being used alone.
MATTERHORN enrolled patients with heart failure and secondary mitral regurgitation in a mixed secondary-MR population (about 84% ventricular secondary MR, with a smaller atrial secondary subgroup). It is therefore not a “ventricular secondary MR–only” trial. M-TEER was found noninferior to mitral-valve surgery for a one-year composite clinical endpoint, and the 30-day composite safety endpoint was lower in the M-TEER group.[10] Noninferiority is not the same as superiority. Being less invasive does not mean M-TEER is a “better” or “safer” treatment for every patient. In some patients, surgery’s ability to address other valves, coronary bypass/coronary surgery or additional anatomical problems in the same operation may be an important advantage. Expected durability and possible future procedures remain part of lifetime planning.
| Decision domain | M-TEER question | Surgical question |
|---|---|---|
| Mechanism | Is leaflet-capture anatomy suitable? | Is durable repair likely? |
| Overall risk | Would a less invasive approach provide meaningful advantage? | Is surgical and recovery risk acceptable? |
| Other disease | Could advanced heart failure limit benefit? | Is bypass or another valve procedure needed? |
| Valve area | Could leaflet approximation create stenosis? | Is repair or replacement more appropriate? |
| Lifetime plan | How would recurrent regurgitation or another procedure be managed? | How will repair durability and reintervention be planned? |
What are the risks of MitraClip?
M-TEER is a valve intervention with potentially serious complications. Individual risk depends on anatomy, heart-failure stage, kidney and lung function, bleeding tendency, rhythm and device system.[1–3]
- Bleeding or vascular-access complications
- Stroke or transient neurological injury
- Cardiac injury and pericardial effusion
- Leaflet injury or single-leaflet device attachment
- Residual or recurrent mitral regurgitation
- Increased mitral gradient or mitral stenosis
- Device migration
- Need for urgent surgery or another procedure
- Arrhythmia, infection, kidney injury or death

Preparing for MitraClip
The complete medicine list, anticoagulants and antiplatelets, allergies, previous bleeding, kidney disease, swallowing or oesophageal problems and possible active infection should be shared with the team. Medicines must not be stopped or started based on online information. Individual instructions for medicines, fasting and arrival time should be followed.[16]
Recovery and follow-up
After the procedure, rhythm, blood pressure, the access site, kidney function and the mitral result are monitored. The need for intensive or close observation, mobilisation and discharge timing varies.[16]
The discharge plan should cover access-site care, gradual activity, lifting, driving and return to work, medicines, heart-failure symptom monitoring, follow-up and echocardiography. MitraClip does not make heart-failure medicines unnecessary; particularly in secondary mitral regurgitation, device and medical treatment are complementary.[1]

How are MitraClip and PASCAL selected?
CLASP IID compared PASCAL with MitraClip in patients with degenerative mitral regurgitation at prohibitive surgical risk. PASCAL met the prespecified noninferiority criterion; two-year numerical differences did not establish a universal device winner.[11–13]
Leaflet length and motion, jet number and location, valve area, expected gradient, calcification and the team’s technical plan guide selection. For a more detailed device comparison, see MitraClip or PASCAL? The CLASP IID trial.
When is urgent help needed?
New weakness of the face, arm or leg, speech difficulty, severe chest pain, fainting, marked breathlessness, cyanosis, uncontrolled groin bleeding or sudden severe deterioration requires urgent assessment. In Türkiye, call 112.[18]
Frequently asked questions
No. M-TEER is usually performed through a catheter introduced from a femoral vein; the breastbone is not opened and the native mitral valve is not removed. It is still a major interventional procedure with important risks.
M-TEER is the general name of the procedure. MitraClip is one device system used to perform it; PASCAL is another M-TEER system.
Duration varies with anatomy, the number of implants and findings during the procedure. One guaranteed duration should not be promised online.
The need for close monitoring and discharge timing are individual. Access-site findings, rhythm, kidney function and the valve result are checked before discharge.[16]
The plan is not the same for everyone. Atrial fibrillation, coronary stents, bleeding risk and other conditions are considered; prescribed medicines should not be changed without the treating team.
Yes. Regurgitation can increase again as heart disease progresses or because of leaflet or device-related changes. Clinical and echocardiographic follow-up remains necessary.
Assessment and decision
The MitraClip decision is not based on one echocardiographic number or surgical risk alone. Mechanism, cardiac response, optimised treatment, valve anatomy, other diseases, surgical options and the patient’s goals are considered together.[1,2]
Literature
References
Praz F, Borger MA, Lanz J, et al. 2025 ESC/EACTS Guidelines for the management of valvular heart disease. European Heart Journal. 2025;46:4635–4736. doi:DOI: 10.1093/eurheartj/ehaf194.
Otto CM, Nishimura RA, Bonow RO, et al. 2020 ACC/AHA Guideline for the Management of Patients With Valvular Heart Disease. Circulation. 2021. doi:DOI: 10.1161/CIR.0000000000000923.
Feldman T, et al. EVEREST II. N Engl J Med. 2011. doi:DOI: 10.1056/NEJMoa1009355. PMID 21463154.
Feldman T, et al. EVEREST II five-year results. J Am Coll Cardiol. 2015. doi:DOI: 10.1016/j.jacc.2015.10.018. PMID 26718672.
Stone GW, et al. COAPT primary report. N Engl J Med. 2018. doi:DOI: 10.1056/NEJMoa1806640. PMID 30280640.
Stone GW, et al. COAPT five-year follow-up. N Engl J Med. 2023. doi:DOI: 10.1056/NEJMoa2300213. PMID 36876756.
Obadia JF, et al. MITRA-FR. N Engl J Med. 2018. doi:DOI: 10.1056/NEJMoa1805374. PMID 30145927.
Iung B, et al. MITRA-FR two-year outcomes. Eur J Heart Fail. 2019. doi:DOI: 10.1002/ejhf.1616. PMID 31476260.
Anker SD, et al. RESHAPE-HF2. N Engl J Med. 2024. doi:DOI: 10.1056/NEJMoa2314328. PMID 39216092.
Baldus S, et al. MATTERHORN. N Engl J Med. 2024. doi:DOI: 10.1056/NEJMoa2408739. PMID 39216093.
Lim DS, et al. CLASP IID primary report. JACC Cardiovasc Interv. 2022. doi:DOI: 10.1016/j.jcin.2022.09.005. PMID 36121247.
Zahr F, et al. CLASP IID one-year outcomes. JACC Cardiovasc Interv. 2023. doi:DOI: 10.1016/j.jcin.2023.10.002. PMID 37962288.
Makkar R, et al. CLASP IID two-year outcomes. JACC Cardiovasc Interv. 2025. doi:DOI: 10.1016/j.jcin.2025.07.014. PMID 41093456.
ClinicalTrials.gov. REPAIR MR — NCT04198870. No results published as of 29 August 2026.
American Heart Association. Options for Heart Valve Repair.
Royal Brompton & Harefield NHS Foundation Trust. Having a MitraClip procedure.
Liv Hospital. Prof. Dr. Hakan Ucar institutional profile. Identity and scope verification only.
Republic of Türkiye, 112 Emergency Call Centre. Official site.
This content is for general information only and does not replace personalized medical advice. In emergencies call local emergency services.
Continue